What Is a Varicocele?
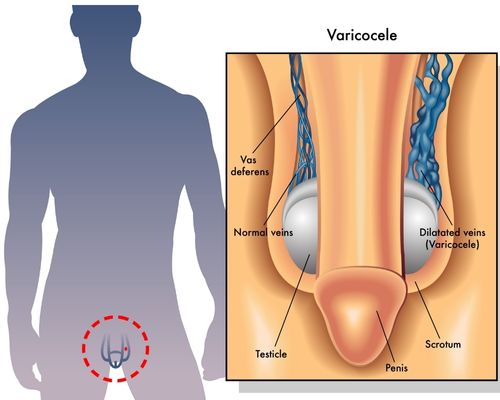
A varicocele is an abnormal enlargement of the veins inside the scrotum, specifically the pampiniform plexus – the network of small veins that surrounds the spermatic cord and drains blood away from each testicle. Think of these veins as a built-in cooling system: by keeping blood moving efficiently, they maintain the slightly lower temperature the testicles need for healthy sperm and testosterone production.
When the one-way valves inside these veins fail, blood pools around the testicles instead of flowing back toward the heart through the gonadal vein. That pooling triggers a cascade of problems:
Increased scrotal temperature, which disrupts sperm development
Higher oxidative stress, damaging sperm DNA
Reduced oxygen delivery to testicular tissue
Build-up of harmful metabolites from the adrenal and kidney veins
Over time, these changes disrupt the delicate environment the testicles need, negatively affecting both fertility and hormone production. At Tower Urology, we diagnose and treat varicoceles with advanced techniques tailored to each patient’s needs.

Who Does a Varicocele Normally Affect?
Varicoceles are far more common than most people realize, and understanding who is at risk is the first step toward protecting your long-term reproductive health. Roughly 15% of all adult males have a varicocele — and that figure rises sharply to approximately 35–40% of men evaluated for infertility, making it the single most correctable cause of male factor infertility. At Tower Urology, we believe no man should lose his fertility to a condition this treatable. Varicoceles most commonly develop between the ages of 15 and 35, typically appearing during or shortly after puberty when blood flow to the reproductive organs increases rapidly.
About 90% of varicoceles occur on the left side because the left gonadal vein drains at a sharp 90-degree angle into the left renal vein—a geometry that makes it significantly harder for blood to flow upward against gravity. Right-sided varicoceles do occur, but a newly identified right-sided varicocele in an adult always warrants imaging to rule out an abdominal mass compressing the vein. This is precisely the kind of detail our specialists are trained to catch.
Bilateral varicoceles — affecting both sides simultaneously — are found in roughly 30–40% of men diagnosed with the condition. Bilateral cases are associated with more pronounced effects on sperm parameters and testicular volume than unilateral cases, and they require a particularly thorough, individualized treatment approach.
Varicocele in Adolescents and Teenagers
Adolescent varicocele deserves special attention, and early, expert evaluation can profoundly affect a young man’s future. The teenage years are precisely when testicular development is most vulnerable — and varicoceles are detected in approximately 14–16% of adolescent males, a prevalence nearly identical to that seen in adults. This tells us something important: in most cases, the condition begins silently during the teen years and progresses without obvious symptoms, making awareness and proactive screening essential.
The primary concern in adolescents is testicular volume loss. A varicocele can impair normal growth of the left testicle during puberty, producing a measurable size difference between the two sides—a condition called hypotrophy. Research consistently shows that successful treatment during adolescence can allow the affected testicle to “catch up” in size, a phenomenon known as catch-up growth. This recovery is rarely observed when treatment is delayed until adulthood, which is why timely evaluation matters. We understand that bringing a teenager in for this kind of conversation requires trust, and we are committed to providing a compassionate, judgment-free environment for young patients and their families.
Current guidelines from the American Urological Association recommend considering treatment in adolescents when any of the following are present:
The affected testicle is more than 20% smaller than the other side
Semen analysis — when age-appropriate — reveals abnormal parameters
The varicocele is bilateral, affecting both sides
The patient experiences significant pain that interferes with daily activity
For teenagers who do not meet these criteria, a structured program of watchful waiting — including annual testicular volume measurements and, where appropriate, periodic semen analysis — is a clinically sound approach. Parents and young patients should understand that monitoring is active, not passive. Missing follow-up appointments can allow silent progression to go undetected until meaningful damage has already occurred. Our team will work closely with your family to ensure that every scheduled check-in is treated with the same urgency and care as any other stage of treatment.
What Causes a Varicocele?
A varicocele develops when the valves inside the spermatic cord veins fail to keep blood moving in one direction. Contributing factors include:
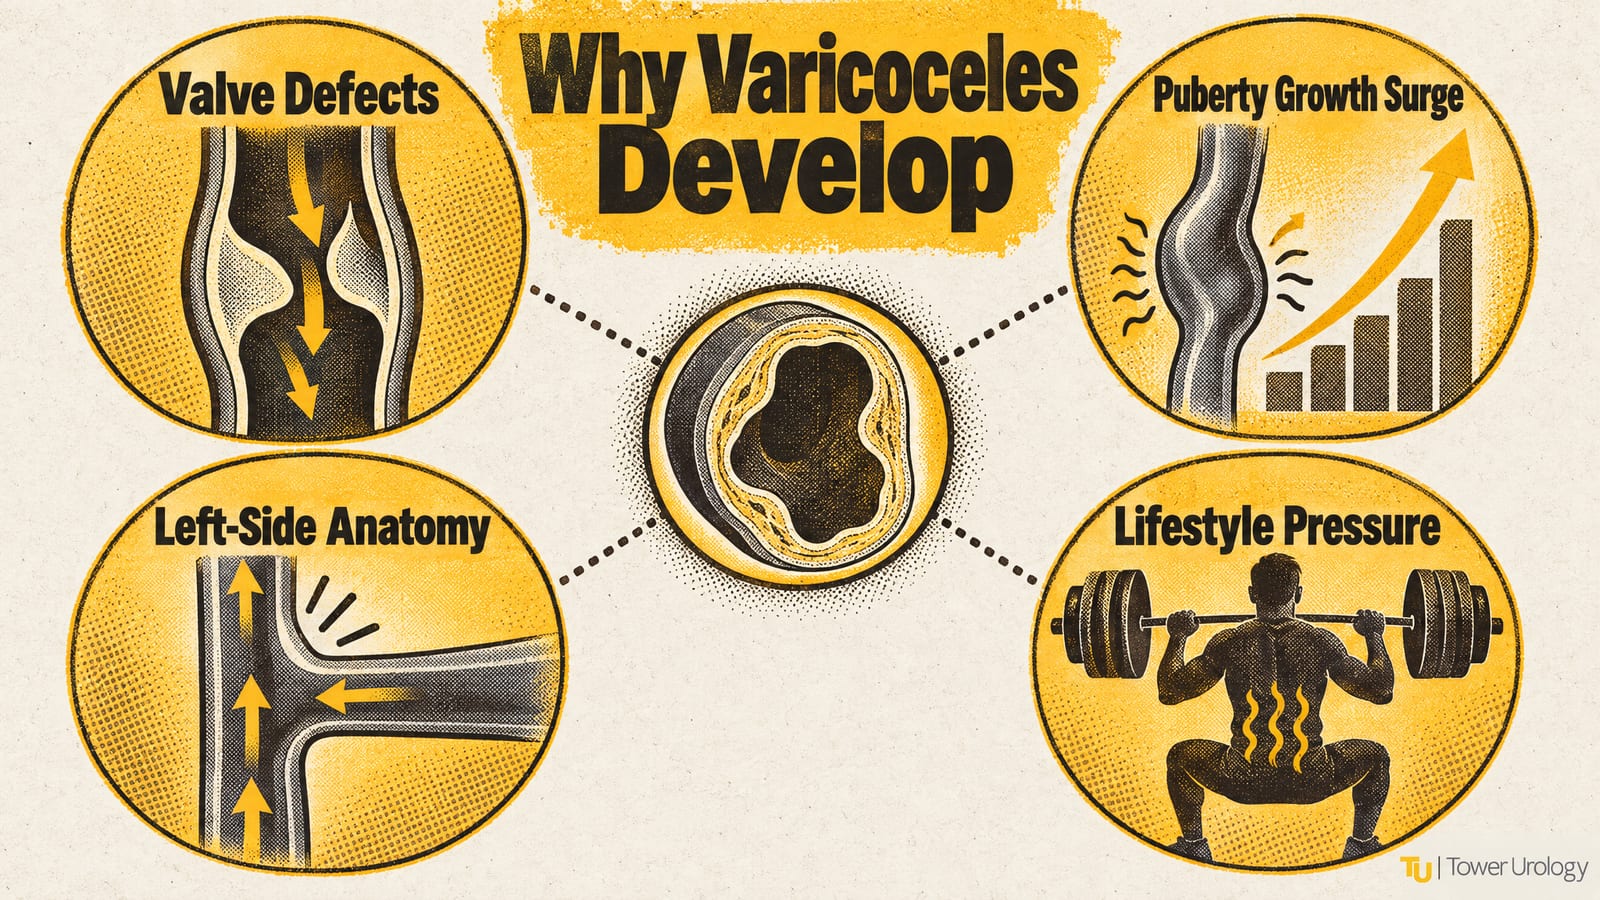
Anatomical valve defects: Absent or incompetent valves in the internal spermatic vein allow blood to reflux downward into the pampiniform plexus.
Puberty-related blood flow changes: Rapid growth during adolescence increases blood flow to the reproductive organs, stressing veins that may already have weak valves.
Left-sided anatomy: The left gonadal vein’s perpendicular insertion into the left renal vein creates higher venous pressure on the left side.
Lifestyle factors: Obesity, prolonged standing, and heavy lifting may increase intra-abdominal pressure and worsen venous reflux.
What Are the Symptoms of a Varicocele?
Many varicoceles cause no symptoms at all and are discovered only during a fertility evaluation or routine physical exam. When symptoms do occur, they typically include:
A noticeable lump or swelling in the scrotum, sometimes described as feeling like a “bag of worms”
A dull, aching, or heavy sensation in the testicle that worsens with prolonged standing or physical activity and improves when lying down
Visible swelling, most often on the left side
Testicular atrophy (shrinkage) over time, particularly in adolescents
Fertility concerns, including difficulty achieving natural conception
The lie-down reduction test: One practical self-check is to lie flat on your back for 10-15 minutes. A true varicocele should noticeably shrink or become less prominent as gravity stops pulling blood into the pampiniform plexus. If the swelling doesn’t reduce when you lie down, seek prompt evaluation, as it may suggest a different underlying cause.
How Are Varicoceles Diagnosed?
At Tower Urology, we combine a thorough physical examination with advanced imaging and, for men with fertility concerns, targeted laboratory testing—giving you a complete, accurate picture of your condition from the first visit.
Physical examination: Your urologist will carefully palpate the scrotum while you are standing, then ask you to perform a Valsalva maneuver (bearing down as if straining). This increases intra-abdominal pressure, making any dilated veins more prominent and easier to assess with precision.
Scrotal ultrasound with Doppler: Ultrasound confirms the diagnosis, measures vein diameter, and detects retrograde blood flow (reflux). Veins wider than 3 mm with reflux on Doppler are diagnostic. Ultrasound also evaluates testicular volume — a particularly important measurement for adolescents and younger men.
Semen analysis: For men with fertility concerns, we evaluate sperm count, motility, and morphology. Sperm DNA fragmentation testing may also be ordered, since varicoceles are a leading cause of elevated DNA damage in sperm — a factor that standard semen analysis alone can miss.
Hormone panel: Testosterone and FSH levels may be checked, particularly when symptoms of low testosterone are present alongside a suspected varicocele.
Varicocele Grading: Understanding Subclinical, Grade I, Grade II, and Grade III
Once a varicocele is confirmed, your Tower Urology specialist will assign a clinical grade using the Dubin and Amelar classification system — the universally accepted standard used by urologists worldwide. Understanding your grade is an important step, because it helps determine how significant the varicocele is and directly informs the most appropriate treatment path for you.
Subclinical varicocele: Not detectable on physical examination; identified only through Doppler ultrasound. The clinical significance of treating subclinical varicoceles remains debated, and most major guidelines do not recommend routine intervention at this stage.
Grade I: A small varicocele that is palpable only during a Valsalva maneuver. It is not visible to the naked eye and may be easy to overlook without a careful, experienced examination.
Grade II: A moderate varicocele that is palpable without a Valsalva maneuver but remains invisible through the scrotal skin.
Grade III: A large varicocele that is visible through the scrotal skin without any special maneuver — often described as the classic “bag of worms” appearance.
Higher grades generally correlate with greater effects on sperm parameters and testicular volume, though even a Grade I varicocele can meaningfully impair fertility in some men. Your grade is never considered in isolation. Our specialists weigh it alongside your semen analysis results, testicular volume measurements, symptom burden, hormone levels, and your personal fertility goals — because we believe every treatment decision should be as individual as the patient in front of us.
Are Varicoceles Dangerous?
Varicoceles are not life-threatening, but they are not harmless either. Their impact depends on grade, duration, and individual biology. Here is what the evidence shows:
Fertility impact: Varicoceles impair sperm production through multiple mechanisms. Elevated scrotal temperature slows sperm development. Oxidative stress damages sperm cell membranes and, critically, causes sperm DNA fragmentation – breaks in the genetic material carried by sperm. High DNA fragmentation reduces fertilization rates, increases miscarriage risk, and diminishes the success of IVF and ICSI cycles. Men with varicoceles consistently show lower sperm count, reduced sperm motility, and higher DNA fragmentation scores than men without varicoceles. That said, eight out of ten men with a varicocele do not experience infertility – the condition exists on a spectrum.
Bilateral vs. unilateral effects: Bilateral varicoceles cause more pronounced damage to sperm parameters than left-sided varicoceles alone, because both testicles are exposed to elevated temperature and oxidative stress. Men with bilateral varicoceles are more likely to have severely impaired semen analyses.
Testosterone and metabolic health: Varicoceles can suppress testosterone production by damaging the Leydig cells responsible for hormone synthesis. In rare but clinically significant cases, this leads to meaningfully low testosterone levels. Chronically low testosterone is associated with metabolic syndrome, insulin resistance, type 2 diabetes, and reduced bone density (osteoporosis). Treating the varicocele has been shown to improve testosterone levels in a meaningful subset of men, which is why hormone evaluation is part of a complete workup.
Right-sided varicocele warning: A varicocele appearing on the right side – or one that does not reduce when lying down – requires imaging to rule out an abdominal or retroperitoneal mass compressing the gonadal vein. This is uncommon but important not to miss.
Varicocele Treatment Options: When to Treat and What to Expect
Not every varicocele requires intervention. The decision to treat depends on a combination of factors, not grade alone. Treatment is generally recommended when one or more of the following apply:
A couple is experiencing infertility and the male partner has abnormal semen parameters (sperm count, motility, or morphology)
Sperm DNA fragmentation is elevated and affecting IVF or ICSI outcomes
Testosterone levels are low and symptomatic
The varicocele causes chronic scrotal pain that affects quality of life
There is evidence of progressive testicular atrophy, particularly in adolescents
When none of these criteria are met, watchful waiting is appropriate. At Tower Urology, we offer every patient a clear, individualized decision framework – not a one-size-fits-all recommendation.
Conservative Management and Watchful Waiting
For men with mild symptoms, normal semen parameters, and no evidence of testicular volume loss, conservative management is a legitimate first step. This approach includes:
Scrotal support: A well-fitted athletic supporter or snug underwear reduces the gravitational pull on the pampiniform plexus and can meaningfully relieve aching discomfort during the day.
NSAIDs for pain: Over-the-counter anti-inflammatory medications such as ibuprofen can manage intermittent scrotal discomfort.
Activity modification: Avoiding prolonged standing, heavy lifting, or activities that worsen symptoms can reduce day-to-day pain.
Monitoring protocol: Watchful waiting is not passive. Men on observation should have a semen analysis every 12 months and a physical exam (with ultrasound if needed) to confirm the varicocele is not progressing. If semen parameters decline or testicular volume decreases, the conversation about intervention should be revisited promptly.
Conservative management does not repair the varicocele or reverse existing damage – it manages symptoms while monitoring for progression.
Varicocelectomy (Microsurgical Repair)
Microsurgical varicocelectomy is the gold-standard treatment for most men who meet criteria for intervention. At Tower Urology, we perform this as a minimally invasive outpatient procedure through very small incisions, using surgical magnification to precisely identify and tie off the dilated veins of the spermatic cord while preserving the testicular artery and lymphatic vessels.
Benefits of microsurgical repair include:
Improved sperm count, motility, and morphology
Significant reduction in sperm DNA fragmentation
Increased natural conception rates
Better outcomes with IVF and ICSI for couples pursuing assisted reproduction
Improved testosterone production in men with low levels
Relief of chronic testicular pain
Realistic complication rates: Microsurgical varicocelectomy has a strong safety profile. Hydrocele formation (fluid accumulation around the testicle) is the most common complication, occurring in roughly 1-2% of microsurgical cases – significantly lower than the 5-10% rate seen with older open surgical techniques. Testicular artery injury is rare (less than 1%) when performed under magnification. Wound infection and hematoma occur in fewer than 1% of cases each.
Recurrence: Varicocele recurrence after microsurgical repair is about 1-2%, substantially lower than the 10-15% recurrence rate associated with conventional open ligation. This is one of the strongest arguments for choosing a microsurgical approach.
Recovery: Most patients return to light activity within a few days and resume full physical activity within two weeks. Scrotal support and avoiding heavy lifting during recovery are recommended.
Varicocele Surgery in Los Angeles
At Tower Urology, varicocele surgery is performed as an outpatient microsurgical varicocelectomy. Using magnification, the surgeon ties off the dilated veins while preserving the testicular artery and lymphatic vessels, which keeps recurrence and hydrocele rates low. For men whose varicocele is affecting fertility, treatment is usually planned alongside a male infertility evaluation, including semen analysis, scrotal ultrasound, and a hormone panel.
Percutaneous Embolization
Varicocele embolization is a non-surgical, image-guided procedure performed by an interventional radiologist. A thin catheter is threaded through a small nick in the skin (usually at the groin or neck) into the gonadal vein, and coils or a sclerosing agent are used to block blood flow through the dilated veins, achieving the same physiological result as surgery without an incision.
Complication rates: Embolization is generally well tolerated. Minor complications such as post-procedure pain or nausea occur in roughly 4-5% of patients. More significant complications – including coil migration or non-target embolization – are rare, occurring in fewer than 1% of cases in experienced hands.
Recurrence: Recurrence rates after embolization are somewhat higher than after microsurgery, ranging from approximately 10-15% in published series, largely because collateral veins can be harder to identify and treat with a catheter-based approach.
Recovery: Most patients resume normal activities within one to two days, making embolization an attractive option for men who want to avoid general anesthesia or a longer recovery.
Some Los Angeles urologists still rely on older open surgical techniques, which carry higher complication and recurrence rates. At Tower Urology, we prioritize the latest minimally invasive and microsurgical approaches to ensure the best possible outcomes.
What Happens If a Varicocele Is Left Untreated?
Leaving a varicocele untreated is not inherently dangerous, but it does carry real risks that depend on the individual’s grade, age, and fertility goals.
For men with normal semen parameters and no symptoms, observation is entirely reasonable. The monitoring protocol described above – annual semen analysis and periodic physical exam – allows the care team to detect any decline before it becomes irreversible.
For men with already-impaired semen parameters, untreated varicoceles are associated with progressive deterioration of sperm count and motility over time. Research suggests that testicular function continues to decline the longer a significant varicocele goes uncorrected, particularly in younger men whose testicles are still developing.
In adolescents, untreated varicoceles with associated testicular hypotrophy carry the highest risk of long-term fertility impairment, because the window for catch-up growth closes as puberty ends.
For men with low testosterone linked to a varicocele, leaving it untreated means the downstream metabolic risks – insulin resistance, metabolic syndrome, reduced bone density – remain in play. Treatment has been shown to improve testosterone in a meaningful proportion of these men, which is a compelling reason not to simply default to testosterone replacement therapy without addressing the underlying cause.
After Treatment: Recovery, Follow-Up, and What to Expect
Understanding what happens after treatment is just as important as choosing the right procedure. Here is what the evidence-based timeline looks like:
Weeks 1-2: Physical recovery. Most men are back to desk work within a few days after microsurgery and within one to two days after embolization. Scrotal support and avoiding strenuous activity protect the surgical site.
Months 1-3: Sperm production begins to improve. Because sperm take approximately 72-90 days to mature (a process called spermatogenesis), improvements in sperm count and motility are not detectable immediately after treatment.
3-month semen analysis: The first post-treatment semen analysis is typically scheduled at three months. This gives a preliminary picture of whether sperm parameters are trending in the right direction.
6-month semen analysis: A second analysis at six months provides a more complete picture. Most studies show the greatest improvements in sperm count, motility, and DNA fragmentation occurring between three and six months post-treatment.
Natural conception window: For couples trying to conceive naturally, most pregnancies that result from varicocele treatment occur within 12-18 months of the procedure.
IVF/ICSI reassessment: For couples already planning assisted reproduction, a post-treatment semen analysis at six months helps determine whether the improvement in sperm quality is sufficient to simplify the IVF protocol or improve ICSI outcomes.
Testosterone follow-up: Men treated for low testosterone related to a varicocele should have hormone levels rechecked at three and six months.
If semen parameters have not improved meaningfully by six months, your Tower Urology team will reassess and discuss next steps, which may include assisted reproductive technology or further evaluation.
Is a Varicocele Commonly Misdiagnosed?
Yes – varicocele symptoms overlap with several other scrotal conditions, and misdiagnosis is more common than patients expect. The three conditions most often confused with a varicocele are:
Epididymitis (inflammation of the epididymis): Causes scrotal pain and swelling, but is typically associated with tenderness localized to the back of the testicle, fever, and sometimes urinary symptoms. It does not reduce when lying down.
Hydrocele (fluid buildup around the testicle): Produces scrotal swelling that transilluminates (light passes through it) and feels smooth and cystic rather than like a tangle of veins. A hydrocele is also a known complication of varicocele surgery when lymphatic vessels are inadvertently disrupted.
Testicular torsion (twisting of the spermatic cord): A urological emergency causing sudden, severe pain. Unlike a varicocele, torsion does not improve with lying down and requires immediate surgical intervention.
Accurate diagnosis at Tower Urology – combining physical examination, the lie-down reduction test, and scrotal Doppler ultrasound – ensures you receive the right treatment plan from the start.
Why Tower Urology Is Your Best Choice for Varicocele Treatment in Los Angeles
At Tower Urology, we take a personalized, evidence-based approach to every varicocele evaluation. We understand that a diagnosis touching on fertility, testosterone, and scrotal health can feel overwhelming – and we are committed to giving you the clinical depth and compassionate guidance you deserve at every step.
We deliver unparalleled expertise and compassionate care to support the best possible outcomes. Our team takes the time to understand your individual situation – your grade, your semen analysis, your fertility goals, your symptoms – and builds a treatment plan around you, not a protocol.
We invite you to establish care with Tower Urology.
Tower Urology is a proud affiliate of Cedars-Sinai Medical Center, ranked #1 in California and #2 nationwide by U.S. News & World Report. This partnership reflects our dedication to delivering the highest standard of urologic care alongside the best urologists in Los Angeles. Our years of experience and access to Cedars-Sinai’s world-class facilities ensure our exceptional, innovative urologic care positions Tower Urology as a leader in Southern California.
Tower Urology is conveniently located for patients throughout Southern California and Los Angeles, including Beverly Hills, Santa Monica, West Los Angeles, West Hollywood, Culver City, Hollywood, Venice, Marina del Rey, Burbank, Glendale, and Downtown Los Angeles.
Our services include treatment for low testosterone, chronic pelvic pain, chronic testicular pain, and Peyronie’s disease.
Varicocele FAQs

Yes, a varicocelectomy can significantly improve fertility outcomes for men with varicoceles. The treatment shows several key benefits:
- Couples have a 30-50% chance of achieving pregnancy after varicocele treatment. The pregnancy success rate is notably higher in treated men compared to those who don’t receive treatment, with the odds of pregnancy increasing by 29%.
- Sperm concentration increases by approximately 12.34 million/ml and sperm quality and motility improve in about 70% of patients.
- Sperm DNA quality improves, with reduced oxidative damage.
Not all varicoceles cause discomfort, but for some men, testicular pain is the symptom that brings them into the clinic. This pain is typically described as:
- A dull, aching heaviness in the scrotum
- Pain that worsens with standing, exercise, or heat exposure
- A dragging or throbbing sensation that improves when lying down
- Occasionally, sharp or intermittent pain occurs in more advanced cases
When pain interferes with quality of life, surgical repair can be both diagnostic (confirming the varicocele as the cause) and therapeutic (providing long-term relief).
Several types of healthcare providers can treat varicoceles, with Urologists being the most common specialists treating varicoceles through surgical methods, particularly for:
- Microsurgical varicocelectomy.
- Laparoscopic surgery.
- Open surgical repair.
Absolutely. Fixing a varicocele is worthwhile for most patients, particularly when experiencing specific symptoms or fertility concerns. Some of the benefits include:
- Success rates of 70-80% with Tower Urology’s microsurgical method.
- Improved semen parameters and pregnancy rates with proper patient selection.
- Enhanced sperm DNA integrity and mitochondrial activity.
- 83% of patients show increased testosterone levels after surgery.
- Even elderly men show improved hormone levels.
No. Varicoceles do not resolve spontaneously. The dilated veins are a structural problem – once the valves fail and the veins enlarge, they do not return to normal without treatment. Symptoms may fluctuate (better when lying down, worse after a long day on your feet), but the underlying varicocele persists. Conservative measures like scrotal support can manage discomfort, but only treatment – surgery or embolization – corrects the problem.
No. Approximately 80% of men with a varicocele are able to father children without any intervention. However, varicoceles are found in 35-40% of men evaluated for infertility, making them the most common correctable cause. The impact on fertility depends on grade, duration, whether the varicocele is unilateral or bilateral, and individual biology. A semen analysis is the most direct way to assess whether your varicocele is affecting sperm production.
Recurrence is possible but uncommon with modern techniques. Microsurgical varicocelectomy has a recurrence rate of approximately 1-2%. Percutaneous embolization has a somewhat higher recurrence rate of 10-15%, primarily because collateral veins can be missed during the catheter-based procedure. If a varicocele recurs, repeat treatment is generally feasible.
For men whose low testosterone is linked to varicocele-related Leydig cell damage, treatment can meaningfully improve testosterone levels. Studies show testosterone improvements in a significant subset of men following varicocelectomy, particularly those with Grade II or III varicoceles and documented low testosterone before surgery. This is one reason we recommend a full hormone panel as part of the initial evaluation – and why treating the varicocele is often preferable to starting testosterone replacement therapy, which can further suppress sperm production.
Because sperm take 72-90 days to mature, meaningful improvements in sperm count and motility typically appear at the three-month semen analysis, with the most significant gains seen by six months. Sperm DNA fragmentation often improves earlier. Most natural conceptions resulting from varicocele treatment occur within 12-18 months of the procedure.
In most cases, yes – when treatment is medically indicated (abnormal semen analysis, testicular atrophy, or significant pain), varicocele repair is covered by major insurance plans. Coverage for embolization versus surgery may vary by plan. Our team at Tower Urology can help you navigate your specific coverage before you commit to a treatment path.
-
30 Varicocele & Infertility Statistics That You Did Not Know
https://www.azuravascularcare.com/infovaricocele/varicocele-infertility-stats -
The Effect of Varicocele Treatment on Fertility in Adults: A Systematic Review and Meta-analysis of Published Prospective Trials
https://pubmed.ncbi.nlm.nih.gov/36151030/ -
The Influence of Varicocelectomy Age on Semen Parameters and Fertility Rates
https://bezmialemscience.org/articles/the-influence-of-varicocelectomy-age-on-semen-parameters-and-fertility-rates/doi/bas.galenos.2023.81905