What are kidney stones?
Kidney stones – medically known as nephrolithiasis or renal calculi – are hard, pebble-like deposits that form inside the kidneys when an imbalance in urine chemistry causes minerals such as calcium, oxalate, and uric acid to crystallize and clump together. They range from a grain of sand to a golf-ball-sized mass, and their behavior depends almost entirely on size.

Stones smaller than 4-5 mm often pass through the urinary tract on their own with adequate fluids and time. Larger stones can become lodged in the ureter – the narrow tube carrying urine from the kidney to the bladder – blocking urine flow and triggering the intense, wave-like cramping known as renal colic. Pain typically starts in the flank or mid-back, just below the rib cage, and radiates toward the lower abdomen and groin as the stone moves. Blood in the urine, nausea, vomiting, and a persistent urge to urinate are also common.
The good news: with the right care and a personalized treatment plan, most people recover fully – and effective prevention strategies can dramatically reduce the risk of recurrence.
How common are kidney stones?
Kidney stones affect more than 10% of adults in the United States during their lifetime, and rates have roughly doubled since the 1970s, driven by rising rates of obesity, diabetes, and dietary changes. This upward trend shows no signs of slowing – researchers attribute much of the increase to the growing prevalence of metabolic conditions, processed food consumption, and chronic dehydration in modern lifestyles.
Men between 40 and 60 remain the highest-risk group, but the gender gap is narrowing: women’s rates have climbed steadily, partly because obesity and diabetes – both independent risk factors – are increasing across all demographics. Dietary shifts toward higher sodium and animal protein intake have also helped push women’s stone rates closer to men’s over the past few decades. In the U.S., prevalence rises from North to South and from East to West, reflecting the role that heat, sweat loss, and concentrated urine play in stone formation.
Types of kidney stones

Not all kidney stones are the same – and knowing your type directly shapes your treatment and prevention plan. There are five main types:
Calcium oxalate – The most common type. Forms when calcium binds with oxalate; linked to high-oxalate diets (spinach, nuts, chocolate) and low fluid intake.
Calcium phosphate – Often associated with renal tubular acidosis or hypercalciuria; can occur alongside calcium oxalate stones.
Uric acid – More common in men; forms when urine is too acidic. Risk factors include a high-animal-protein diet, gout, and excessive alcohol consumption, which raises uric acid levels while reducing urine output.
Struvite – Infection stones composed of magnesium, ammonium, and phosphate. They grow rapidly from urinary tract infections that produce ammonia and can cause serious complications if untreated.
Cystine – The rarest type, caused by cystinuria, a hereditary condition in which the kidneys excrete excess cystine. These stones recur and often require long-term specialist management.
At Tower Urology, our team uses comprehensive metabolic testing and imaging to identify exactly which type you have – so your care plan is built on precision, not guesswork.
What are the symptoms of kidney stones?
A small stone sitting quietly in the kidney often causes no symptoms at all – many people discover one incidentally during imaging for something else. Symptoms begin when a stone breaks free and enters the ureter.
Most patients then experience renal colic – sudden, intense cramping that comes in waves and shifts as the stone moves. It typically starts in the flank or mid-back and radiates toward the lower abdomen and groin. Common symptoms include:
Severe pain in the side, back, or lower abdomen
Pain or burning during urination
Frequent urge to urinate
Blood in the urine (pink, red, or brown)
Nausea and vomiting
Certain symptoms are red flags requiring emergency care. Fever or chills alongside flank pain can signal a kidney infection (pyelonephritis) or a blocked, infected kidney – a serious medical emergency. Inability to keep fluids down, uncontrolled pain, or a complete inability to urinate also warrant immediate attention rather than a scheduled appointment.
What are the common risk factors for kidney stones?

In the United States, kidney stone prevalence increases from North to South and East to West – a pattern driven largely by heat, sweat loss, and the concentrated urine that results.
Common causes of kidney stones include obesity, diabetes, inadequate fluid intake, and diets high in salt, sugar, and animal protein.
Dehydration and climate. Concentrated urine leaves less room for minerals to stay dissolved. People in hot, dry climates – including Southern California – face elevated risk, especially in summer.
Diet. High sodium raises urinary calcium. Excess animal protein raises uric acid and lowers citrate, a natural stone inhibitor. Excess fructose has also been linked to higher stone rates.
Obesity and diabetes. Both alter how the body handles calcium, oxalate, and uric acid. Insulin resistance is strongly associated with uric acid stones.
Family history and prior stone history. If a parent or sibling has had kidney stones, your risk is significantly higher. Having had one stone yourself roughly doubles the likelihood of forming another within five to seven years. Inherited conditions such as cystinuria or primary hyperoxaluria cause recurrent stones and warrant specialized evaluation.
Medical conditions. Hyperparathyroidism releases excess calcium into the bloodstream and urine. Inflammatory bowel disease and bowel surgery increase oxalate absorption. Gout, chronic urinary tract infections, and renal tubular acidosis also contribute.
Medications. Certain drugs raise stone risk, including thiazide diuretics (when used long-term in high doses), calcium-based antacids, the seizure medication topiramate, and high-dose vitamin C supplements. If you take any of these regularly, mention it to your urologist during your evaluation.
How do our urologists diagnose kidney stones?
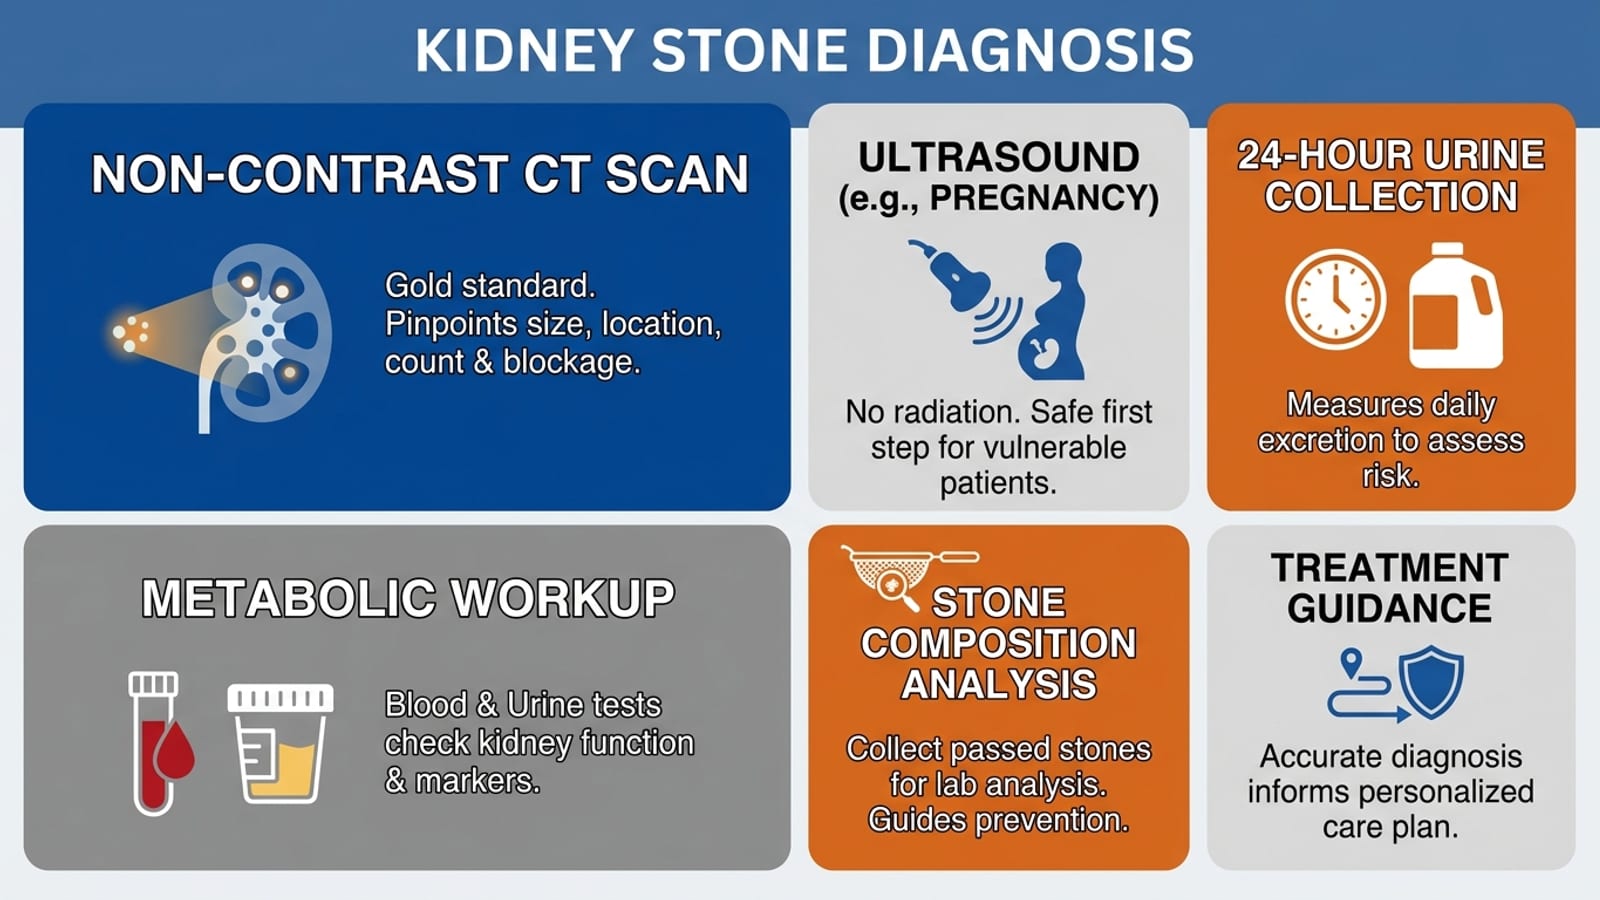
A non-contrast CT scan is the gold-standard imaging tool, pinpointing a stone’s exact size and location, identifying how many stones are present, and revealing whether the ureter is blocked. During pregnancy, doctors use ultrasound instead to avoid radiation exposure.
Imaging is paired with blood and urine tests – including a urinalysis and metabolic workup – to check kidney function, calcium, uric acid, and other markers that explain why a stone formed. A 24-hour urine collection measures what your kidneys are excreting over a full day, giving a clearer picture of your stone-forming risk.
If you pass a stone at home, strain your urine through a fine mesh or coffee filter and bring the stone to your appointment. Stone composition analysis – a lab test identifying whether it is calcium oxalate, uric acid, struvite, cystine, or another type – is one of the most valuable tools for preventing future stones. The results directly inform every dietary and medical recommendation your urologist makes going forward.
When a stone is removed during a procedure such as ureteroscopy or PCNL, our team routinely sends the retrieved fragments to the lab for the same compositional analysis. Knowing exactly what your stone is made of allows our urologists to tailor a personalized prevention plan – whether that means adjusting your diet, increasing hydration, or managing an underlying metabolic condition, so you’re not simply treated and discharged, but genuinely protected against recurrence. This comprehensive, detail-oriented approach to diagnosis sets Tower Urology’s fellowship-trained endourology team apart.
How do we treat kidney stones?
Tower Urology’s fellowship-trained endourology specialists take a personalized approach, matching each patient to the right treatment based on stone size, location, composition, and overall health. Treatment generally falls into one of two pathways – watchful waiting with medical support or minimally invasive intervention – and your urologist will guide you toward the option most likely to deliver the best possible outcome for your specific situation.
Watchful waiting and medical expulsive therapy
Not every kidney stone requires a procedure, and stone size is one of the most reliable guides to whether yours will pass on its own. Stones smaller than 4 mm pass without intervention in most cases, typically within one to two weeks. Stones in the 4-10 mm range fall into a middle ground – your urologist will weigh your symptoms, the stone’s location in the urinary tract, and how your body is responding before recommending a path forward. Stones larger than 10 mm rarely pass without some form of treatment.
For patients who are good candidates for watchful waiting, the plan centers on staying well hydrated – enough fluid to produce at least two liters of urine per day – and straining urine to catch the stone for laboratory analysis. Stone composition matters: knowing whether you passed a calcium oxalate, uric acid, or struvite stone directly shapes your prevention plan. Most stones pass within two to four weeks of symptoms starting.
Pain management is an important part of this period, and your care team will discuss appropriate options to keep you comfortable while you wait. If pain becomes severe, is accompanied by fever or chills, or you can’t keep fluids down, contact your urologist promptly; these are signs that watchful waiting may no longer be the right approach. Your urologist may also prescribe an alpha-blocker such as tamsulosin, a strategy called medical expulsive therapy, which relaxes the smooth muscle lining the ureter, widening the passage and meaningfully improving passage rates for stones sitting in the lower ureter.
If your stone does not pass within the expected window, or if your symptoms worsen, our team will reassess and discuss minimally invasive options such as ureteroscopy or laser lithotripsy to resolve it with as little disruption to your daily life as possible.
Minimally invasive and surgical treatments
When a stone is too large to pass, is causing a blockage, leads to infection, or simply isn’t moving despite conservative management, Tower Urology offers all common and advanced treatments:
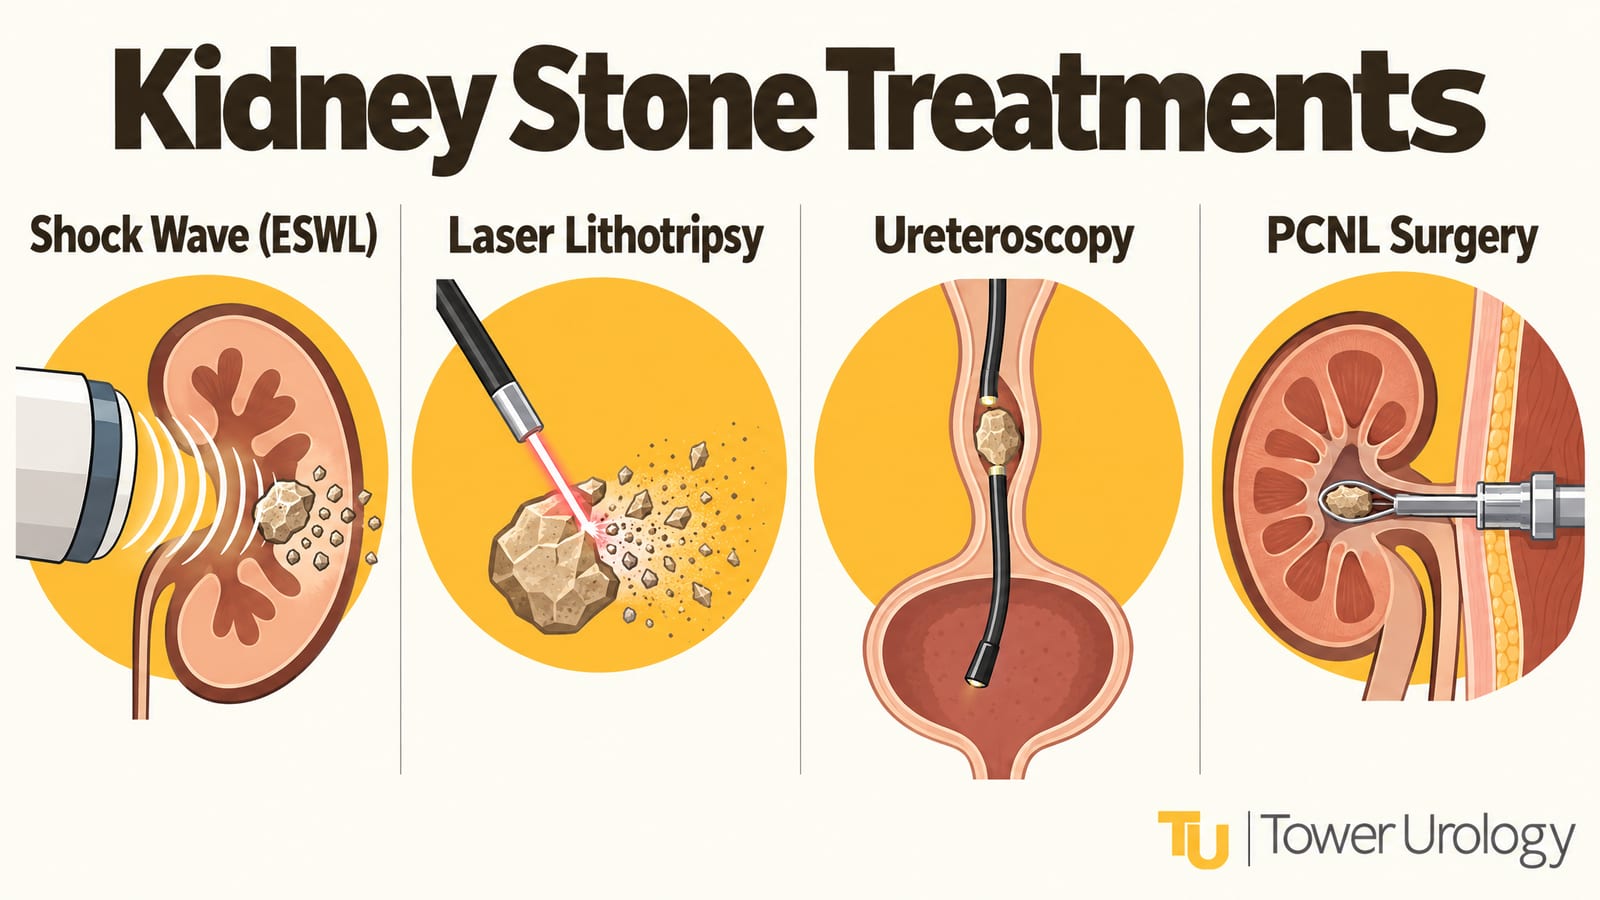
Extracorporeal Shock Wave Lithotripsy (ESWL) – High-energy shock waves break the stone into smaller fragments that pass naturally through urine. A non-invasive outpatient procedure well suited to stones in the kidney or upper ureter.
Laser Lithotripsy – A laser breaks stones into very small pieces that can be removed at the same time or passed in urine.
Ureteroscopy – A ureteroscope allows the surgeon to see inside the ureter and remove or fragment stones near the bladder. No incisions are required; it is particularly effective for mid- and lower-ureter stones.
Percutaneous Nephrolithotomy (PCNL) – A minimally invasive surgical approach for large stones (generally over 20 mm) or those that have not responded to other treatments. Recovery is faster than with traditional open surgery, and most patients return to normal activity within a few weeks.
What are the complications of kidney stones?
Most kidney stones pass on their own without causing lasting harm, but when they don’t, the consequences can be serious. Understanding what’s at stake is one more reason to take kidney stones seriously and get personalized care from a specialist sooner rather than later.
Here are the most important complications to be aware of:
Urinary tract infections (UTIs) and kidney infections. A stone blocking urine flow creates the perfect environment for bacteria to multiply. What starts as a bladder infection can quickly travel up to the kidneys, causing a condition called pyelonephritis – which is far more difficult to treat than a standard UTI.
Sepsis. If a kidney infection goes untreated, bacteria can enter the bloodstream and trigger sepsis – a life-threatening, whole-body inflammatory response. This is one of the primary reasons a blocked kidney with signs of infection is considered a urological emergency.
Hydronephrosis. When a stone blocks urine from draining out of the kidney, the kidney can swell as fluid backs up. This swelling, called hydronephrosis, puts pressure on delicate kidney tissue and can cause significant pain. If left unresolved, it can lead to permanent damage.
Chronic kidney disease and permanent kidney damage. Repeated episodes of kidney stones – or a single prolonged obstruction – can gradually scar kidney tissue and reduce kidney function over time. In severe cases, this may contribute to chronic kidney disease.
If you’re unsure whether you’re dealing with a complication, our team at Tower Urology can help you figure out whether you need a urologist or a nephrologist, and connect you with the right specialist fast.
What are the complications of kidney stones?
Most kidney stones resolve without lasting harm, but untreated or recurrent stones can lead to serious complications:
Kidney infection (pyelonephritis) and sepsis. A stone that blocks urine flow can trap bacteria, causing a kidney infection that may progress to sepsis – a life-threatening systemic response. This is the most urgent complication and the primary reason fever with flank pain demands emergency evaluation.
Hydronephrosis. Prolonged blockage causes urine to back up and the kidney to swell. If the obstruction is not relieved, the pressure can permanently damage kidney tissue.
Chronic kidney disease (CKD). Repeated episodes of obstruction, infection, or inflammation can gradually reduce kidney function over time, increasing the risk of CKD.
Permanent kidney damage. In severe or long-standing cases – particularly with struvite stones, which grow rapidly – irreversible loss of kidney function is possible without prompt treatment.
Recurrent urinary tract infections. Struvite stones in particular are both caused by and perpetuate UTIs, creating a cycle that requires complete stone removal to break.
These risks underscore why even a manageable stone deserves a proper evaluation. Early treatment protects your long-term kidney health.
How can you prevent kidney stones?
Prevention is one of the highest-value conversations you can have with your urologist – especially if you have already had one stone, since recurrence risk is significant without targeted changes.
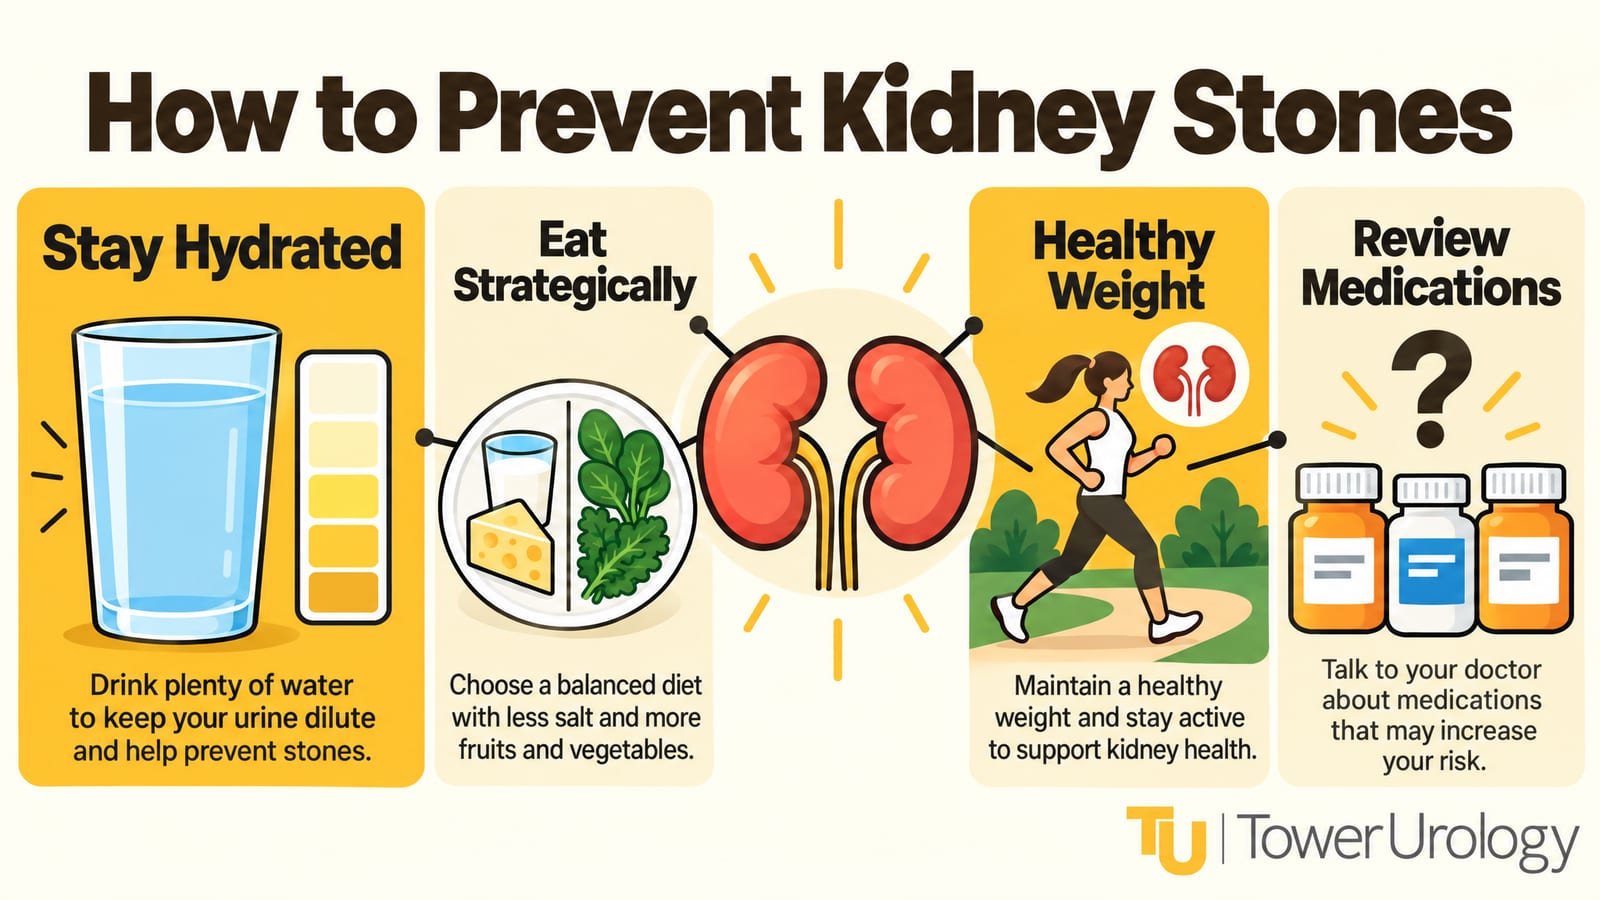
Stay well hydrated. This is the single most effective step. Aim for urine that looks pale yellow throughout the day – roughly 2.5 to 3 liters of fluid daily for most adults. If you live in a warm climate like Los Angeles or exercise regularly, you need more to compensate for sweat loss. Lemon juice and other citrate-rich beverages can help: citrate naturally inhibits stone formation, and potassium citrate is also available as a prescription supplement for patients who need a more targeted approach.
Adjust your diet strategically. If you are prone to calcium oxalate stones, limit high-oxalate foods (spinach, nuts, chocolate) and pair calcium-rich foods with meals rather than avoiding calcium altogether – dietary calcium binds oxalate in the gut and prevents it from reaching the kidneys. Reduce sodium, since a high-salt diet raises urinary calcium. For uric acid stones, cutting back on red meat, shellfish, and alcohol, especially beer and spirits, which raise uric acid and reduce urine output simultaneously, can meaningfully lower risk.
Maintain a healthy weight. Obesity and insulin resistance are independent risk factors. Regular physical activity and a balanced diet support your kidneys as much as the rest of your body.
Review your medications. If you take calcium-based antacids, high-dose vitamin C, or topiramate, discuss stone risk with your doctor – adjustments or alternatives may be appropriate.
After a stone episode, the team at Tower Urology can analyze your stone composition and 24-hour urine chemistry to build a prevention plan tailored specifically to you.
When should you see a doctor or go to the ER?
Not every kidney stone is an emergency, but some situations require immediate care. Go to the emergency room or call 911 if you experience:
Fever or chills alongside flank or back pain – this combination can indicate a blocked, infected kidney and can progress to sepsis rapidly
Uncontrolled pain that does not respond to over-the-counter medication
Inability to keep fluids down due to persistent vomiting
Complete inability to urinate
Signs of severe dehydration
Schedule an urgent (non-ER) appointment with a urologist if you have your first episode of kidney stone symptoms, if a stone has not passed after four weeks, if you have a known single kidney or reduced kidney function, or if you are experiencing recurrent stones. Early evaluation leads to better outcomes – and gives you the information you need to prevent the next one.
At Tower Urology, our fellowship-trained endourology specialists are ready to guide you from diagnosis through recovery and prevention, delivering unparalleled expertise and compassionate care at every step. We serve patients throughout Los Angeles, including Beverly Hills, Santa Monica, West Hollywood, Culver City, Burbank, Glendale, and Downtown Los Angeles. Our broader services include treatment for urinary bladder dysfunction, hematuria, urinary tract infections, incontinence, and overactive bladder.
Kidney Stone FAQs

If you’re dealing with kidney stones, you’ll typically see a urologist. Urologists specialize in kidney stones and treat diseases of the urinary tract (kidneys, ureters, bladder, and urethra) and the reproductive system.
They diagnose, manage, and treat kidney stones.
Patients with recurrent or chronic kidney stones may benefit from seeing a urologist experienced in treating active stones and identifying the underlying causes of stone formation. When choosing a specialist, patients may want to consider access to advanced imaging technology, minimally invasive treatment options, metabolic stone evaluation, and long-term prevention strategies.
At Tower Urology, patients can access experienced urologists who provide comprehensive kidney stone care, including diagnostic evaluation, minimally invasive stone treatment, and personalized prevention plans designed to reduce the risk of future stones.
We always tell our patients that the best way to manage their kidney stones is to do whatever it takes to prevent them from forming. Treating kidney stones isn’t hard, but making the necessary dietary and lifestyle changes to prevent future stone formation isn’t always easy.
However, the best approach is to work with your urologist to devise a treatment plan to prevent them.
Yes, kidney stones can increase the risk of developing chronic kidney disease (CKD). People with kidney stones have nearly twice the risk of developing CKD compared to those without kidney stones. Long-term studies confirm this relationship, showing that kidney stone formers have a 51% to 68% increased risk of CKD by diagnostic codes and a 25% to 44% increased risk by elevated serum creatinine levels.
Managing chronic or recurrent kidney stones often involves more than simply treating active stones. Long-term management may include identifying underlying causes, evaluating diet and hydration habits, performing metabolic testing, and developing personalized prevention strategies to reduce the risk of future stone formation.
Depending on stone size, location, and frequency, treatment may include increased hydration, dietary changes, medications, or minimally invasive procedures to remove stones when necessary. At Tower Urology, patients receive comprehensive kidney stone care focused on both effective treatment and long-term prevention.
It depends on size. Stones under 4 mm often pass within one to two weeks. Larger stones may take longer or require treatment to help them along.
Most are not life-threatening, but untreated stones can cause kidney infections, hydronephrosis, sepsis, and long-term kidney damage. Fever with flank pain is always a reason to go to the ER right away.
Yes. Without lifestyle changes, roughly half of people who have had one stone will develop another within five to seven years. Personalized prevention – including stone analysis, dietary changes, and sometimes potassium citrate – can significantly reduce that risk.
Not always. Many stones pass naturally with hydration and pain management. When intervention is needed, our team offers minimally invasive options – ESWL, laser lithotripsy, ureteroscopy, and PCNL – designed for faster recovery and reduced discomfort.
Absolutely. While kidney stones are slightly more common in men, women are affected too – and their symptoms can sometimes be mistaken for other conditions. Our experienced female urologists in Los Angeles provide compassionate, comprehensive care tailored specifically to women’s urological health.