What Is a Vasectomy?
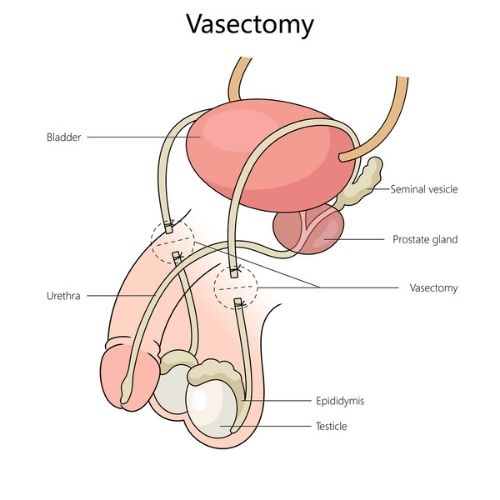
A vasectomy is a surgical procedure for permanent birth control in men. It works by cutting, tying, or blocking the vas deferens – the two small tubes that carry sperm from the testicles to the urethra.
Once those tubes are sealed, sperm can no longer mix with semen during ejaculation, making pregnancy virtually impossible. It is one of the most common elective procedures in the United States, with roughly 500,000 men choosing a vasectomy every year.
Vasectomy is considered a permanent form of contraception. It does not affect testosterone levels, sex drive, or the ability to have an erection. The only change is that semen no longer contains sperm – and because sperm make up only a tiny fraction of ejaculate volume, there is no noticeable difference in the amount or appearance of semen after the procedure.
How Does a Vasectomy Work?
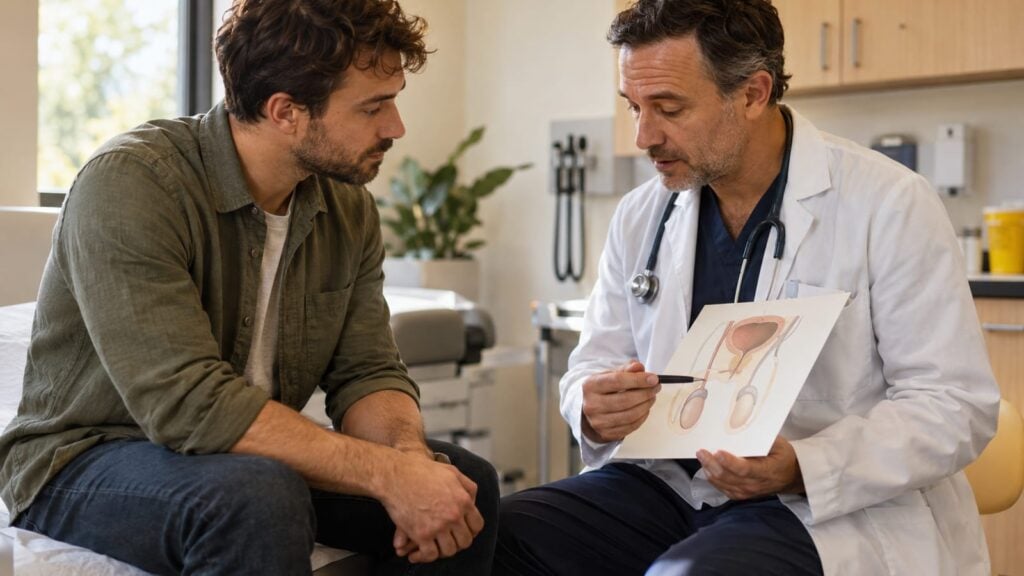
To understand how a vasectomy works, it helps to know a little about the anatomy involved. Sperm are produced in the testicles and travel through two small tubes called the vas deferens on their way to mix with seminal fluid before ejaculation. A vasectomy simply interrupts that journey by cutting, blocking, or sealing each vas deferens so sperm can no longer reach the semen.
After the procedure, sperm are still produced in the testicles – that part does not change. But with nowhere to go, the body naturally breaks them down and absorbs them. Testosterone production is completely unaffected, so there is no impact on sex drive, erections, or orgasms.
It is worth noting that a vasectomy does not work instantly. Sperm that were already further along in the reproductive tract before the procedure can still be present for several weeks afterward. That is why a follow-up semen analysis – typically done about eight to sixteen weeks post-procedure – is an important step to confirm the vasectomy has been fully effective. Until that test comes back showing zero motile sperm, another form of contraception is still needed.
Types of Vasectomy: Conventional vs. No-Scalpel
There are two main ways a vasectomy is performed, and both achieve the same result. The difference is in how the surgeon reaches the vas deferens.
The conventional approach uses a small scalpel to make one or two incisions in the scrotum to access the vas deferens. The vas deferens is then cut, tied, or sealed before the incisions are closed with sutures.
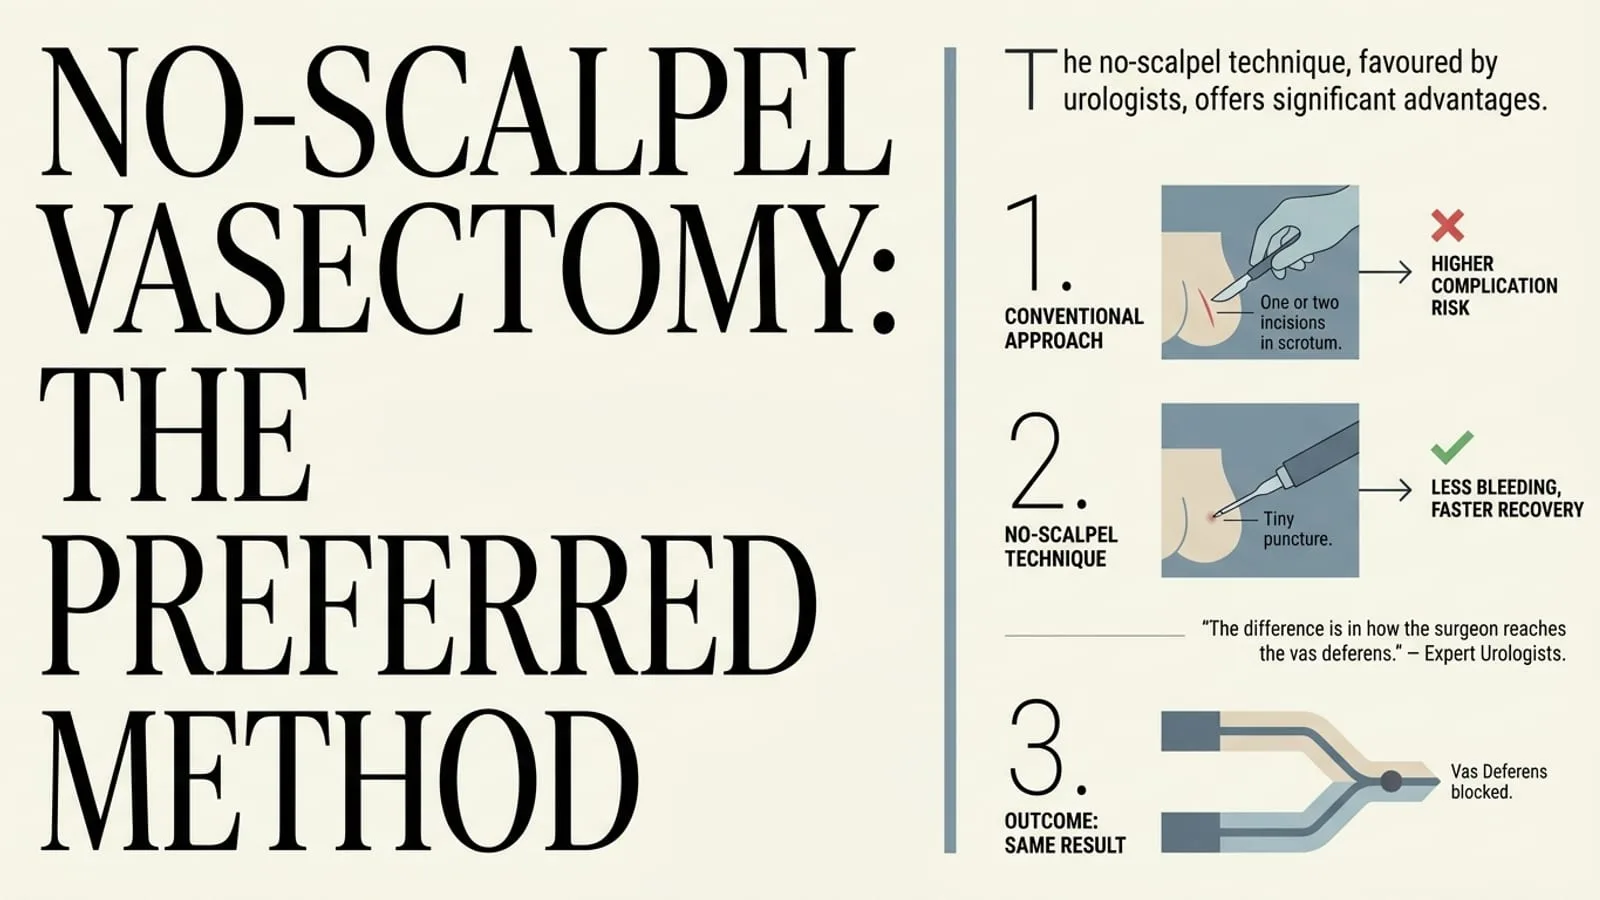
The no-scalpel technique – now the preferred method among urologists – uses a tiny puncture instead of a cut. Specialized instruments gently stretch the skin opening and lift out the vas deferens, then seal it and return it to position. Because the opening is so small, stitches are not needed. This approach means less bleeding, a lower risk of complications, and a faster recovery. Multiple studies have also shown that the no-scalpel method offers better vas occlusion – that is, more reliable sealing of the vas deferens – resulting in a lower failure rate than other sealing forms such as simple suture or clip ligation.
Both procedures are outpatient procedures performed under local anesthesia, and patients go home the same day.
Tower Urology’s No-Scalpel Vasectomy: How We Do It
At Tower Urology, we specialize in the no-scalpel technique, offering men in Los Angeles a safe, effective, and virtually painless option for long-term family planning. Here is how the procedure works, step by step.
No-needle anesthesia
A local anesthetic is administered using a jet injector, eliminating the need for traditional needles. This device delivers a fine, high-pressure stream of anesthetic through the skin, providing effective numbing without the discomfort of a needle stick – one of the most anxiety-provoking parts of the procedure for many men.
No-scalpel access
A small opening is made in the scrotum using specialized instruments instead of a traditional incision. Your doctor will gently stretch the skin of this opening to access the vas deferens – the tubes that carry sperm.
Sealing the vas deferens
The vas deferens is sealed using a technique shown in research to provide superior occlusion compared to simple clip or suture ligation, resulting in a lower failure rate. The sealed tubes are then returned to their position.
Quick and minimally invasive
The entire procedure takes less than 30 minutes. Because the opening is so small, stitches aren’t needed, and most men go home the same day feeling comfortable.
How Effective Is a Vasectomy?
Vasectomy is one of the most reliable forms of contraception available, with success rates exceeding 99%. The key factor in effectiveness is the occlusion – the sealing – of the vas deferens, which is consistent across both conventional and no-scalpel techniques. However, occlusion studies show the no-scalpel approach has a lower failure rate than clip or suture ligation methods, making it the preferred choice for most urologists today.
Sterility is not immediate after the procedure. Sperm already present in the reproductive tract must be cleared before the vasectomy is considered effective. A follow-up semen analysis at approximately eight to sixteen weeks – or after roughly 20 ejaculations – is the only reliable way to confirm success. Skipping this step is one of the most common reasons for unintended pregnancy after vasectomy.
Safety and Risks: What to Know Before You Decide
Vasectomy is a highly safe procedure, and the no-scalpel technique carries a lower overall complication rate than conventional incision methods. That said, as with any medical intervention, there are some risks worth understanding before you decide.
Mild discomfort at the surgical site is the most common experience and typically resolves within a few days with rest and over-the-counter pain relief.
Hematoma – a collection of blood near the surgical site – is the most frequently reported complication, occurring in roughly 1 to 2% of no-scalpel vasectomies compared to up to 4 to 5% with conventional techniques. Applying an ice pack and wearing supportive underwear in the first 48 hours significantly reduces this risk.
Infection affects fewer than 1% of patients and is usually mild, responding quickly to a short course of antibiotics.
Sperm granuloma, a small, firm nodule that can form if sperm leaks from the sealed vas deferens, occurs in approximately 3 to 4% of cases. It is generally harmless and often resolves on its own, though it can occasionally cause localized tenderness.
Post-vasectomy pain syndrome (PVPS) is a chronic scrotal discomfort that affects an estimated 1 to 2% of men to a degree that impacts daily life. Mild, intermittent aching is more common but usually manageable without intervention.
Procedural failure – where fertility is not fully interrupted – occurs in fewer than 1 in 2,000 cases, which is why a follow-up semen analysis is a standard part of the process.
Who Is a Good Candidate for a Vasectomy?
The ideal candidate for a vasectomy is a man who is certain he does not want biological children in the future and is seeking a minimally invasive, highly effective option for permanent contraception. Most healthy adult men are suitable candidates. However, a vasectomy is not the right choice for everyone, and understanding the situations where it may not be appropriate is an important part of making a fully informed decision.
There are very few absolute medical contraindications to vasectomy, but some conditions do require extra caution or may rule it out entirely:
Active genital infection or skin condition: Any current infection in the scrotal area – such as epididymitis or a skin infection – needs to be fully resolved before the procedure can safely go ahead.
Bleeding disorders or anticoagulant use: Men on blood thinners or with clotting disorders face a higher risk of post-procedure bleeding and hematoma. Your doctor will review your medications carefully beforehand.
Anatomical abnormalities: Conditions like prior scrotal surgery, varicocele, hydrocele, or a significantly thickened vas deferens can make the procedure more technically challenging and may require a modified approach. You can learn more about scrotal anatomy concerns in our overview of microsurgical varicocelectomy vs. varicocele embolization.
Uncertainty about the decision: This is not a medical contraindication, but it is just as important. Vasectomy should be considered permanent. If you have any doubt about wanting biological children in the future, it is worth pausing and discussing your options thoroughly with your urologist.
If any of these situations apply to you, you may be able to address them before scheduling the procedure. The key is an open, thorough consultation so your provider can tailor the approach to your specific circumstances.
How to Prepare for Your Vasectomy
Once you have decided a vasectomy is right for you, a little preparation goes a long way toward making the procedure and recovery as smooth as possible. No hospital stay, no general anesthesia, and most men are back on the couch the same day.
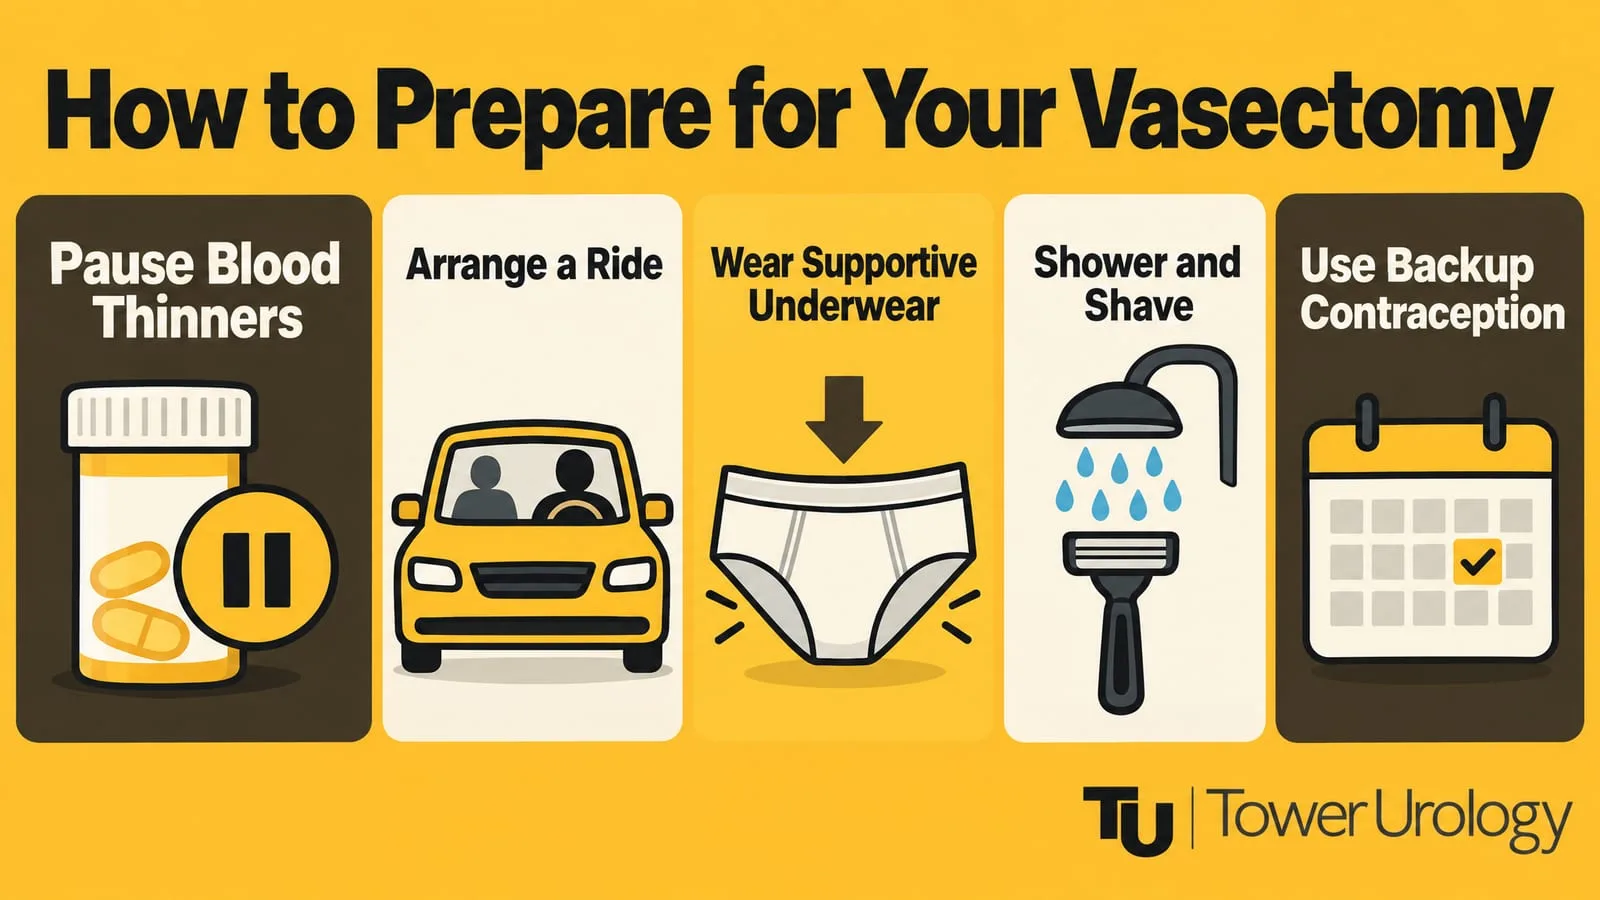
Here is what to take care of in the days leading up to your appointment:
Stop blood thinners and certain supplements. If you take aspirin, ibuprofen, naproxen, or prescription blood thinners, talk to your doctor about pausing them for about a week before the procedure. Fish oil, vitamin E, and some herbal supplements can also increase bleeding, so mention everything you are taking at your consultation.
Arrange a ride home. Even though the procedure is quick and you will be awake the whole time, you will have local anesthesia on board and some scrotal tenderness afterward. We strongly recommend having someone drive you home.
Wear supportive underwear. On the day of your vasectomy, wear snug, supportive underwear – briefs or a jockstrap work well. Good support minimizes movement and helps keep swelling and discomfort down after the procedure. Keep wearing supportive underwear for the first few days of recovery, too.
Shower and shave the area. Shower the morning of your appointment and gently shave the scrotal area if your provider asks you to. Clean skin reduces infection risk and helps the procedure go more smoothly.
Plan for a quiet day or two. Stock the freezer with ice packs, set up a comfortable spot on the couch, and plan to take it easy for 48 hours. Most men take a long weekend and feel ready to return to a desk job by Monday. Strenuous activity and heavy lifting should wait about a week.
Plan for post-procedure contraception. A vasectomy is not immediately effective. Plan to use a backup method until your doctor gives you the all-clear, typically after about 8 to 16 weeks or 20 ejaculations. Skipping this step is one of the most common reasons for unintended pregnancy after the procedure.
What to Expect on the Day of Your Vasectomy
The procedure itself is straightforward and usually takes about 15 to 30 minutes in an outpatient setting. You will be awake the whole time – local anesthesia numbs the area so you feel pressure but not pain. At Tower Urology, we use a jet injector to deliver the local anesthetic, eliminating the need for a traditional needle and making the experience more comfortable from the first step.
With the no-scalpel approach, the urologist makes a tiny puncture in the scrotum rather than an incision, locates each vas deferens, and blocks or removes a small segment. Because the opening is so small, no stitches are needed. Most men spend the rest of the day resting with an ice pack and return to a desk job within two to three days.
Recovery: What to Expect After Your Vasectomy
The first 48 hours
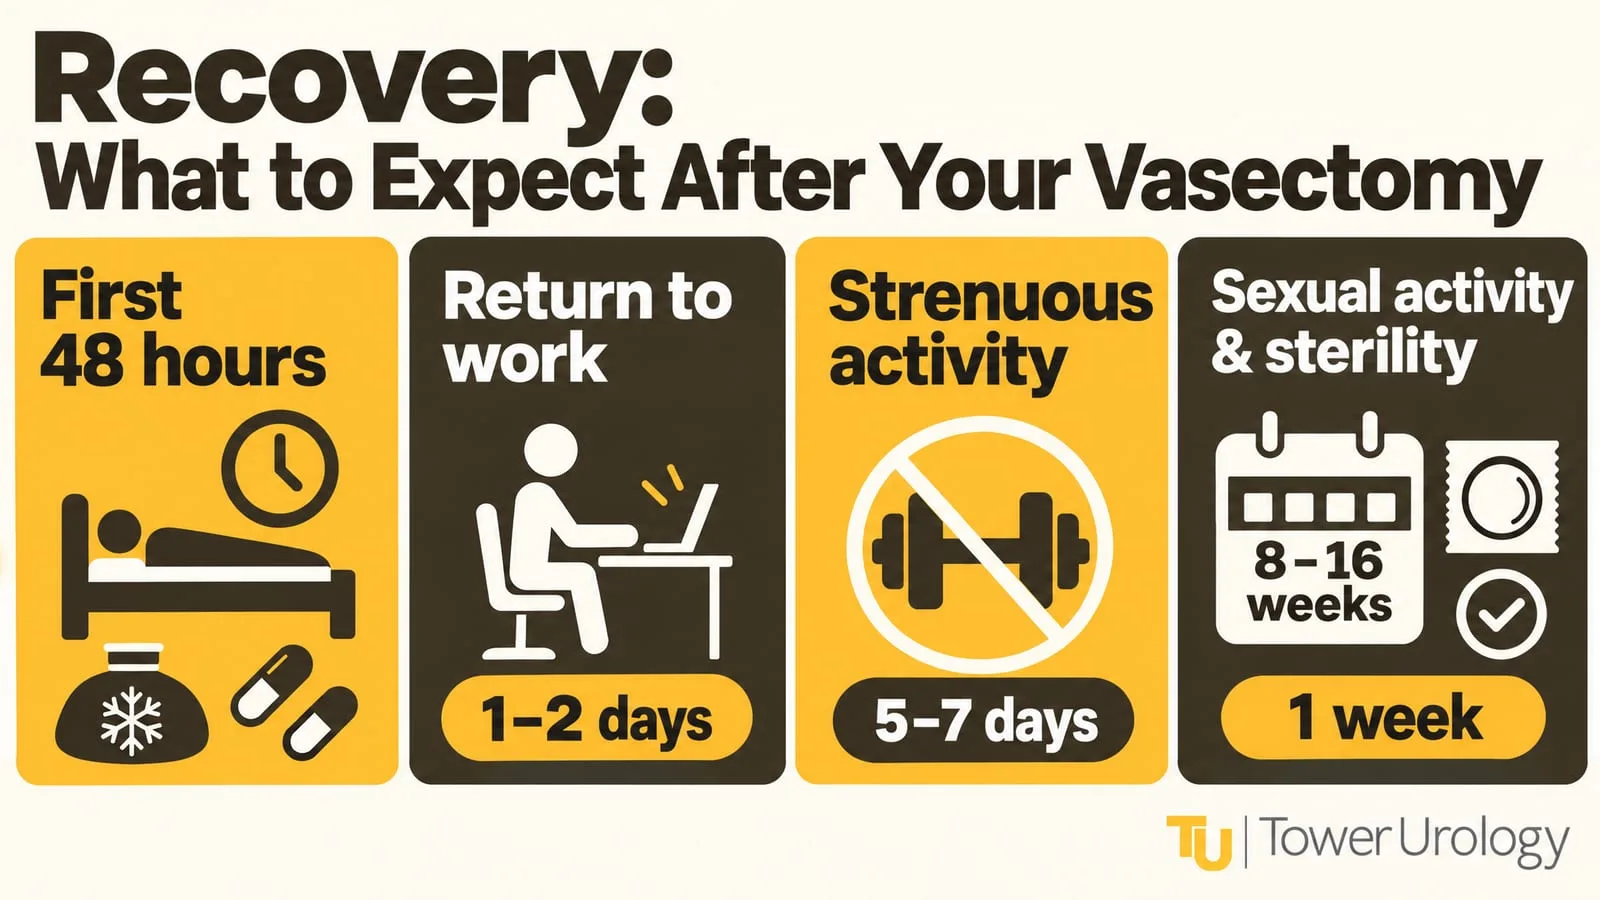
Plan to rest for the rest of the day after your procedure, and avoid standing or walking for extended periods that first evening. Apply an ice pack intermittently to your scrotum for the first 24 hours to manage swelling. Over-the-counter pain relief is usually enough for mild discomfort.
Returning to work and light activity
Most men can return to a desk job and engage in light physical activity within one to two days. You may notice mild swelling or bruising, which is normal and typically resolves within a week.
Returning to strenuous activity
Avoid heavy lifting, vigorous exercise, and strenuous physical labor for at least five to seven days. Most men are fully back to the gym or physically demanding jobs within a week, but it’s best to listen to your body and ease back in gradually.
Resuming sexual activity and confirming sterility
Sexual activity can usually be resumed after one week. However, it is essential to use contraception until a follow-up semen analysis confirms the absence of motile sperm. The AUA Guideline recommends scheduling that semen analysis at approximately eight to sixteen weeks after your procedure, or after roughly 20 ejaculations – whichever comes later. Once your follow-up analysis returns a result of zero motile sperm, you can safely discontinue other contraception. Until you receive that confirmation, always use a backup method.
Can a Vasectomy Be Reversed?
Yes, a vasectomy can be reversed through a procedure called a vasovasostomy, where a surgeon reconnects the two cut ends of the vas deferens. However, you should understand a few important things before you count on reversal as a backup plan.
Success rates vary quite a bit depending on how much time has passed since the original vasectomy:
Reversal within 3 years: sperm return rates of around 75% or higher
Reversal after 3 to 8 years: success rates begin to decline noticeably
Reversal after 15 or more years: success rates can drop to 30% or lower
Even when sperm do return after reversal, achieving a pregnancy is not guaranteed. Factors that influence male fertility, like your partner’s age and fertility, also play a significant role in the outcome.
Cost is another major consideration. Vasectomy reversal is a microsurgical procedure that typically costs several thousand dollars and is rarely covered by insurance. Compared with the relatively low cost of the original vasectomy, the financial math rarely works in reversal’s favor. If there is any real chance you will want biological children in the future, sperm banking before your vasectomy is worth discussing with your urologist.
The bottom line is that a vasectomy should always be treated as a permanent decision. If you are curious about factors that can affect male fertility more broadly, that context can also help you think through your options.
Vasectomy vs. Tubal Ligation: Comparing Permanent Contraception Options
When a couple decides they are done having children, two permanent options usually come up: vasectomy for the male partner or tubal ligation for the female partner. Both are highly effective, but they differ in procedure complexity, recovery time, cost, and risk.
In terms of effectiveness, both procedures are over 99% effective at preventing pregnancy, so neither has a meaningful edge. They differ in how they are performed. A vasectomy is an outpatient procedure done under local anesthesia that typically takes about 15 to 30 minutes. Tubal ligation, on the other hand, requires general anesthesia and involves entering the abdominal cavity, making it a more invasive surgery with a longer recovery period of one to two weeks compared to just a few days for most vasectomy patients.
Cost is another significant difference. Vasectomy typically costs $300 to $1,300 out of pocket, while tubal ligation can run $6,000 to $10,000 without insurance when you factor in surgical facility fees, anesthesia, and follow-up care. From a purely practical standpoint, vasectomy carries a lower complication risk as well, since it avoids the risks associated with general anesthesia and abdominal surgery.
Neither procedure should be entered into lightly, since both are intended to be permanent. That said, if you are weighing your options as a couple, vasectomy is generally the simpler, safer, and more affordable path to permanent contraception. Talking through the decision with a urologist – and, if needed, your partner’s OB-GYN – is always a smart first step.
Why Choose Tower Urology in Los Angeles?
At Tower Urology, we take a personalized, evidence-based approach to urologic care. All our professionals are committed to providing expert care and thorough follow-up. We take the time to understand you and personalize your treatment plan, delivering unparalleled expertise and compassionate care to support the best possible outcomes.
Tower Urology is a proud affiliate of Cedars-Sinai Medical Center, ranked #1 in California and #2 nationwide by U.S. News and World Report. This partnership reflects our dedication to delivering the highest standard of urologic care alongside Los Angeles’s best urologists. Our years of experience and access to Cedars-Sinai’s world-class facilities ensure our exceptional, innovative urological care positions Tower Urology as a leader in Southern California.
Tower Urology is conveniently located for patients throughout Southern California and Los Angeles, including Beverly Hills, Santa Monica, West Los Angeles, West Hollywood, Culver City, Hollywood, Venice, Marina del Rey, Burbank, Glendale, and Downtown Los Angeles.
Our services include treatment for low testosterone, chronic pelvic pain, chronic testicular pain, and Peyronie’s disease.
We invite you to establish care with Tower Urology. Call us or request your appointment online:
Vasectomy FAQs

A vasectomy is a surgical procedure that permanently prevents pregnancy by blocking the vas deferens – the tubes that carry sperm from the testicles to the urethra. Once blocked, sperm can no longer mix with semen during ejaculation. The procedure is performed under local anesthesia as an outpatient procedure and takes about 15 to 30 minutes.
A vasectomy does not work immediately. Sperm already stored beyond the blockage site remains in your reproductive tract and must be cleared out first. Most urologists ask you to use a backup contraceptive method for at least 8 to 16 weeks after the procedure, or until a post-vasectomy semen analysis confirms a zero sperm count. That follow-up test is the only reliable way to know the procedure worked. Skipping it is one of the most common reasons for unintended pregnancy after vasectomy.
The procedure is straightforward and usually takes about 15 to 30 minutes in an outpatient setting. You will be awake the whole time – local anesthesia numbs the area so you feel pressure but not pain. With a no-scalpel approach, the urologist makes a tiny puncture rather than an incision, locates each vas deferens, and blocks or removes a small segment. Most men spend the rest of the day resting with an ice pack and return to a desk job within two to three days. Mild soreness and minor swelling are normal; report significant pain or swelling to your doctor.
Technically, yes, but you should treat it as permanent. A vasectomy reversal (vasovasostomy) is a microsurgical procedure that reconnects the vas deferens. Success rates are highest when the reversal is done within three years of the original vasectomy – roughly 75% of couples achieve pregnancy – but that rate drops significantly the longer you wait, falling to around 30% or less after 15 years. Reversal surgery is also considerably more expensive than the original procedure and is rarely covered by insurance. If there is any real chance you will want biological children in the future, sperm banking before your vasectomy is worth discussing with your urologist.
A vasectomy does not affect your sex drive or ability to get erections. Your testosterone levels and sexual function remain the same because only the tubes that carry sperm are sealed – nothing else changes. Most men notice no difference in libido or erections after the procedure. If you do experience changes, they are usually due to stress or unrelated issues, not the vasectomy itself.
Current research shows that vasectomy is linked to a slight increase in the relative risk of being diagnosed with prostate cancer – about 10 to 18% higher relative risk. However, the absolute risk increase is very low, and studies do not show a higher risk of aggressive or fatal prostate cancer after vasectomy. Most medical organizations do not consider this a reason to avoid a vasectomy, but it is a good idea to discuss any concerns with your doctor.
A vasectomy is generally considered a safe procedure with a low risk of long-term problems. Most men do not experience noticeable side effects, and serious health issues are rare. Potential long-term considerations include post-vasectomy pain syndrome (PVPS), which affects about 1 to 2% of men and can last months or years, and rare issues such as delayed vasectomy failure or sperm granulomas. Overall, long-term physiological health – including hormone levels and cancer risk – appears unaffected for the vast majority of men.
The cost of a no-scalpel vasectomy in the United States typically ranges from $300 to $1,300 if you are paying out of pocket. Most health insurance plans cover part or all of the cost, so your out-of-pocket expense may be limited to a copay or coinsurance. Medicaid and some state programs may also cover the procedure for eligible individuals, potentially making it free or very low cost. By comparison, tubal ligation can cost $6,000 to $10,000 without insurance, making vasectomy the significantly more affordable option for permanent contraception.
We believe patient experiences speak for themselves. Explore real stories and outcomes from men treated at our Los Angeles practice on our men’s health testimonials page.
Sources
-
Vasectomy: AUA Guideline
https://doi.org/10.1016%2Fj.juro.2012.09.080 -
A Review of 10 Years of Vasectomy Programming and Research in Low-Resource Settings | Global Health: Science and Practice
https://doi.org/10.9745%2FGHSP-D-16-00235 -
Vasectomy Regret or Lack Thereof
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC9476225 -
Scalpel versus no-scalpel incision for vasectomy
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6464377